Mole Removal and Benign Skin Lesion Removal in Singapore
Doctor-performed mole removal and skin lesion removal
Benign skin lesions such as milia, skin tags, syringomas, warts, and benign moles are extremely common. While medically harmless, they can cause cosmetic concern and irritation, especially when they change in appearance or occur on visible areas like the face, neck, or eyelids.
At The Skin Longevity Clinic, removal of benign skin lesions is approached as a medical dermatological procedure, with accurate diagnosis, precise removal, and a strong emphasis on skin integrity and scar minimisation.
When is mole removal or skin lesion removal needed?
Removal may be considered when a skin lesion:
Is cosmetically bothersome
Causes friction, irritation, or bleeding (e.g. skin tags)
Has increased in size, number, or prominence
Interferes with daily activities ( e. g. shaving, wearing jewellery, makeup)
Causes diagnostic uncertainty or patient anxiety
Requires confirmation of benign nature before observation
Importantly, not all lesions should be removed blindly. Correct identification is essential to ensure safe and appropriate treatment.
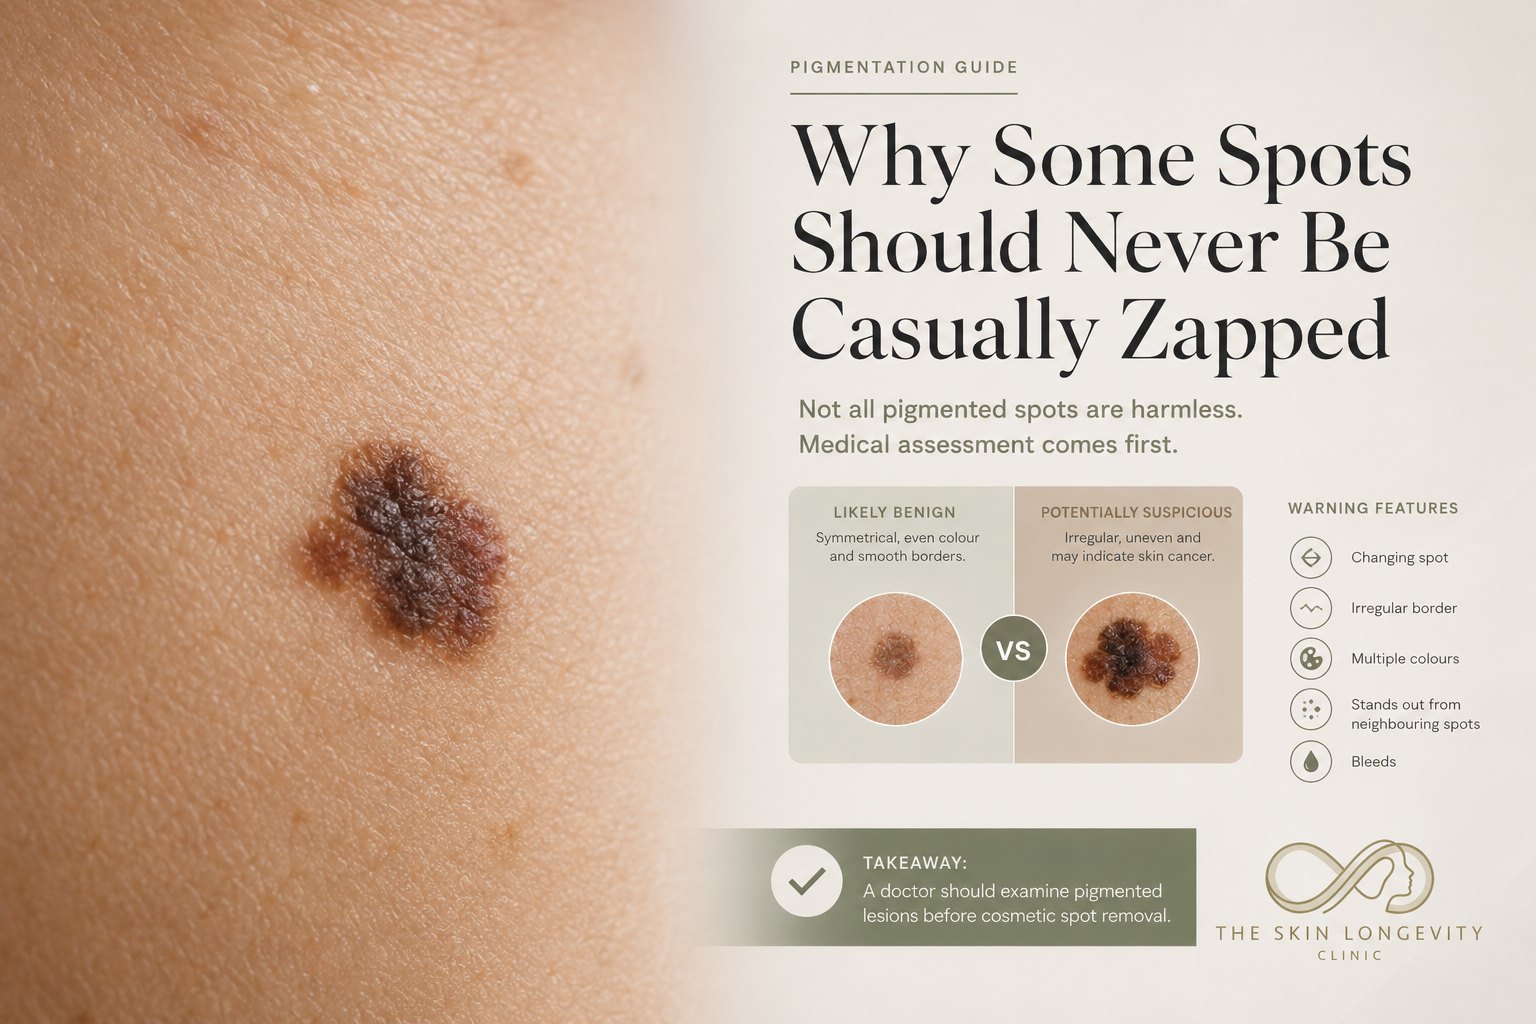
Every mole is examined before removal is offered. The assessment covers symmetry, border, colour, diameter and any recent change, together with the patient’s history of sun exposure, previous skin cancer and family history of melanoma. Dermoscopy, a handheld magnified light that shows pigment patterns below the skin surface, improved the accuracy of melanoma diagnosis by 49 per cent over the naked eye in a meta-analysis of 27 studies, although only when used by experienced examiners.1 The moles (melanocytic naevi) guide explains which changes in a mole to watch for. A mole with features suspicious for melanoma is referred to a dermatologist or plastic surgeon. For benign lesions, the removal method depends on the lesion’s type, depth and site. Carbon dioxide (CO2) laser or electrosurgery suits raised, superficial lesions. Surgical excision is used when the whole lesion should be removed intact and sent for histology, because laser and electrosurgery destroy the tissue and leave nothing to examine under the microscope.2
Mole removal in Singapore: every mole is assessed before the removal method is chosen.
CO2 laser mole removal
Benign raised moles, skin tags, milia, syringomas and seborrhoeic keratoses are removed at the clinic with a CO2 laser under local anaesthetic. The laser’s infrared beam is absorbed by water in the skin cells, which vaporises the lesion one thin layer at a time and seals small blood vessels as it goes, so bleeding is minimal and no cutting or stitches are needed. Most lesions are removed in a single session, and a larger or deeper mole may need a second pass once the first has healed. Evidence for laser removal of small benign moles in Asian skin comes mainly from case series. In one Korean series of 65 small moles treated with an ablative erbium laser followed by an alexandrite laser, visible pigment cleared from every mole, mild atrophic scarring occurred in 10.8 per cent, and pigment returned in 1.5 per cent over six months.3
Electrosurgery and radiofrequency removal of skin tags and small lesions
Electrosurgery, also called radiofrequency or electrodesiccation, uses a fine electrode carrying a high-frequency current to cut through tissue and seal it in one step. It is used for skin tags, small raised moles and some seborrhoeic keratoses, particularly where a lesion hangs on a narrow stalk or bleeds easily. For seborrhoeic keratoses, its clearance rate and patient satisfaction match those of CO2 laser.5 The treated spot heals in 7 to 10 days.
Surgical excision of moles with histology
Surgical excision removes the whole mole with a small margin of normal skin under local anaesthetic, and the wound is closed with fine stitches. The specimen is sent to the laboratory, where histology (microscopic examination of the tissue) confirms the diagnosis. Excision is used for deeper or larger moles, moles that have recurred after laser, lesions for which the patient or doctor wants a tissue diagnosis, and cysts. It leaves a fine linear scar, usually about three times the length of the mole, because the wound is cut as an ellipse so that it closes flat. Stitches are removed at 5 to 14 days depending on the site. Lesions with features suspicious for melanoma are referred rather than excised at the clinic.
Skin tag, milia and syringoma removal
Skin tags (acrochordons) are cut at the base with the CO2 laser or electrosurgery, and multiple tags on the neck, eyelids, underarms or groin can be cleared in one session.
Milia, small cysts filled with keratin, are opened at the surface with the laser and the contents expressed.
Syringomas, benign sweat-duct growths that sit deep in the dermis around the eyes, are treated with a low-energy pinhole CO2 technique over two to three sessions, because aggressive ablation at that depth risks scarring. In a prospective series of 29 Asian patients, two pinhole sessions two months apart improved the lesions by more than half in 17 patients, with near-total clearance in 7.4
Seborrhoeic keratoses and dermatosis papulosa nigra (small, dark, raised spots on the cheeks and neck that are common in darker skin) are flat-ablated with the CO2 laser at low energy to limit darkening afterwards. A randomised comparison of four methods on facial seborrhoeic keratoses found CO2 laser, erbium laser and electrosurgery equally effective, and all three more effective than freezing (cryotherapy).5 A small Japanese case series of dermatosis papulosa nigra treated with CO2 laser reported complete removal without scarring or relapse at one year.6
When a mole should be excised or referred instead of lasered
Laser and electrosurgery are not used on moles with irregular borders, more than one colour, a diameter over 6 mm, recent growth, bleeding or itch. The same applies to moles on the palms, soles or nails, congenital moles larger than a few centimetres, and any lesion whose diagnosis is uncertain.1,2 Destroying such a lesion removes the tissue needed to rule out melanoma, and laser treatment of congenital moles carries high reported rates of scarring and returning pigment, with no high-quality long-term evidence of benefit.2 These lesions are excised so the tissue can be examined, or referred where melanoma is suspected. Flat brown patches such as freckles, sun spots and melasma are not moles and are treated on the pigmentation treatment pathway, where pico laser is used for flat pigment that is not a mole.
Warning signs that mean a mole is examined before any removal.
Mole removal recovery and aftercare
The treated spot is a small, shallow wound that forms a scab and heals over 7 to 14 days. An antibiotic or barrier ointment is applied for the first week to keep the wound moist and clean. Sun avoidance and daily sunscreen for three months limit post-inflammatory hyperpigmentation, the darkening that healing skin in Asian patients readily develops under Singapore’s year-round high ultraviolet (UV) index. Make-up can be worn once the scab has separated.
Mole removal risks in Asian skin
The most common risk is post-inflammatory hyperpigmentation, which is more frequent in darker skin and after sun exposure during healing. Other risks include a small depressed or pale mark where a deeper mole was removed, infection if the wound is picked, and partial regrowth when pigment cells extend below the treated depth. Home mole and skin-tag removers sold online, which contain concentrated salicylic acid, bloodroot or other caustic agents, have caused burns, ulceration and permanent scarring, including injuries next to the eye, and are not a substitute for assessment.7
What affects mole removal cost in Singapore
Mole removal cost depends on the number, size and depth of the lesions, the method used, and whether a second session or histology is needed. A quote is given after the skin check.
Mole removal FAQs
Does mole removal with a laser leave a scar?
A flat or slightly pale mark can remain, most often where a deep or large mole was removed. Small raised moles and skin tags usually heal with little visible trace when the sun is avoided during healing.
Can every mole be removed with a laser?
Laser is used only for moles assessed as benign and superficial. Deeper moles and those needing a diagnosis are surgically excised and sent for histology, and moles suspicious for melanoma are referred.1,2
Is laser, electrosurgery or excision best for mole removal?
Each method suits a different lesion. CO2 laser gives fine control of depth for raised superficial lesions, electrosurgery suits skin tags and stalked lesions, and excision is used when the whole lesion must be examined. For seborrhoeic keratoses, laser and electrosurgery give equivalent results.5 The method is chosen at the skin check.
Will the mole grow back after laser removal?
Partial regrowth can occur when pigment cells remain deeper in the skin, and in one series pigment returned in 1.5 per cent of small moles within six months.3 A second session treats regrowth, and a mole that recurs more than once is excised for histology.
How many syringomas or skin tags can be removed in one visit?
Multiple skin tags and small lesions are usually treated in one session under local anaesthetic. Syringomas around the eyes are spread over two to three sessions to limit scarring.4
Is mole removal painful?
A local anaesthetic injection or cream is used, so the laser, electrode or excision itself is not felt. Mild soreness for a day or two is usual.
Mole removal assessment at The Skin Longevity Clinic
Every mole, skin tag or growth is examined before removal is offered. Dr Rachel Ho matches the method to the lesion: CO2 laser or electrosurgery for raised benign lesions, and surgical excision with histology when the tissue must be examined.
The approach at the clinic is diagnosis-first:
examine every lesion before treatment
refer any mole with features suspicious for melanoma
protect healing skin from the sun to limit darkening
Assessments take place at Scotts Medical Center, 9 Scotts Road. Book through the contact page or call +65 6514 2688.
Selected References
Kittler H, Pehamberger H, Wolff K, Binder M. Diagnostic accuracy of dermoscopy. Lancet Oncol. 2002;3(3):159–165. doi:10.1016/s1470-2045(02)00679-4.
Eggen CAM, Lommerts JE, van Zuuren EJ, et al. Laser treatment of congenital melanocytic naevi: a systematic review. Br J Dermatol. 2018;178(2):369–383. doi:10.1111/bjd.16094.
Lee SE, Choi JY, Hong KT, et al. Treatment of acquired and small congenital melanocytic nevi with combined Er:YAG laser and long-pulsed alexandrite laser in Asian skin. Dermatol Surg. 2015;41(4):473–480. doi:10.1097/DSS.0000000000000288.
Lee SJ, Goo B, Choi MJ, et al. Treatment of periorbital syringoma by the pinhole method using a carbon dioxide laser in 29 Asian patients. J Cosmet Laser Ther. 2015;17(5):273–276. doi:10.3109/14764172.2015.1027224.
Zaresharifi S, Robati RM, Dadkhahfar S, et al. Efficacy and safety of cryotherapy, electrodesiccation, CO2 laser, and Er:YAG laser in the treatment of seborrheic keratosis. Dermatol Ther. 2021;34(5):e15083. doi:10.1111/dth.15083.
Furukawa F, Mizawa M, Shimizu T. Treatment of dermatosis papulosa nigra using a carbon dioxide laser. J Cosmet Dermatol. 2020;19(10):2572–2575. doi:10.1111/jocd.13309.
Konkel K, Reyes M, Diak IL, et al. Serious Skin Injuries Following Exposure to Unapproved Mole and Skin Tag Removers. J Clin Aesthet Dermatol. 2023;16(1):14–17. PubMed.