Bruxism in Singapore: Teeth Grinding, Jaw Clenching and Care
Bruxism is jaw muscle activity that can involve teeth grinding, clenching or holding the jaw tense, during sleep or while awake1. Care focuses on its consequences, such as tooth damage, discomfort or difficulty using the jaw, rather than assuming every episode requires treatment1,2.
A useful consultation starts with what is troubling you most. Waking with a sore jaw, noticing a chipped tooth and being told you grind in your sleep may lead to different priorities.
What is the difference between awake and sleep bruxism?
Awake bruxism involves repeated or sustained tooth contact, or bracing the jaw even without the teeth touching1. Sleep bruxism involves rhythmic or sustained chewing muscle activity during sleep, and the two patterns can coexist1.
Awake and sleep bruxism occur at different times and are assessed differently.
Pattern
What you may notice
What the assessment considers
Awake bruxism
Clenching or holding the jaw tense during concentration or stressful moments
Awareness, frequency, discomfort and situations associated with the behaviour2,3
Sleep bruxism
Grinding reported by a partner, morning muscle fatigue or dental changes
Dental findings, symptoms and whether further sleep assessment is relevant2,3
The 2025 international consensus describes bruxism as a motor behaviour rather than automatically classifying it as a disorder1. The clinical question is whether it is contributing to a problem that needs attention1.
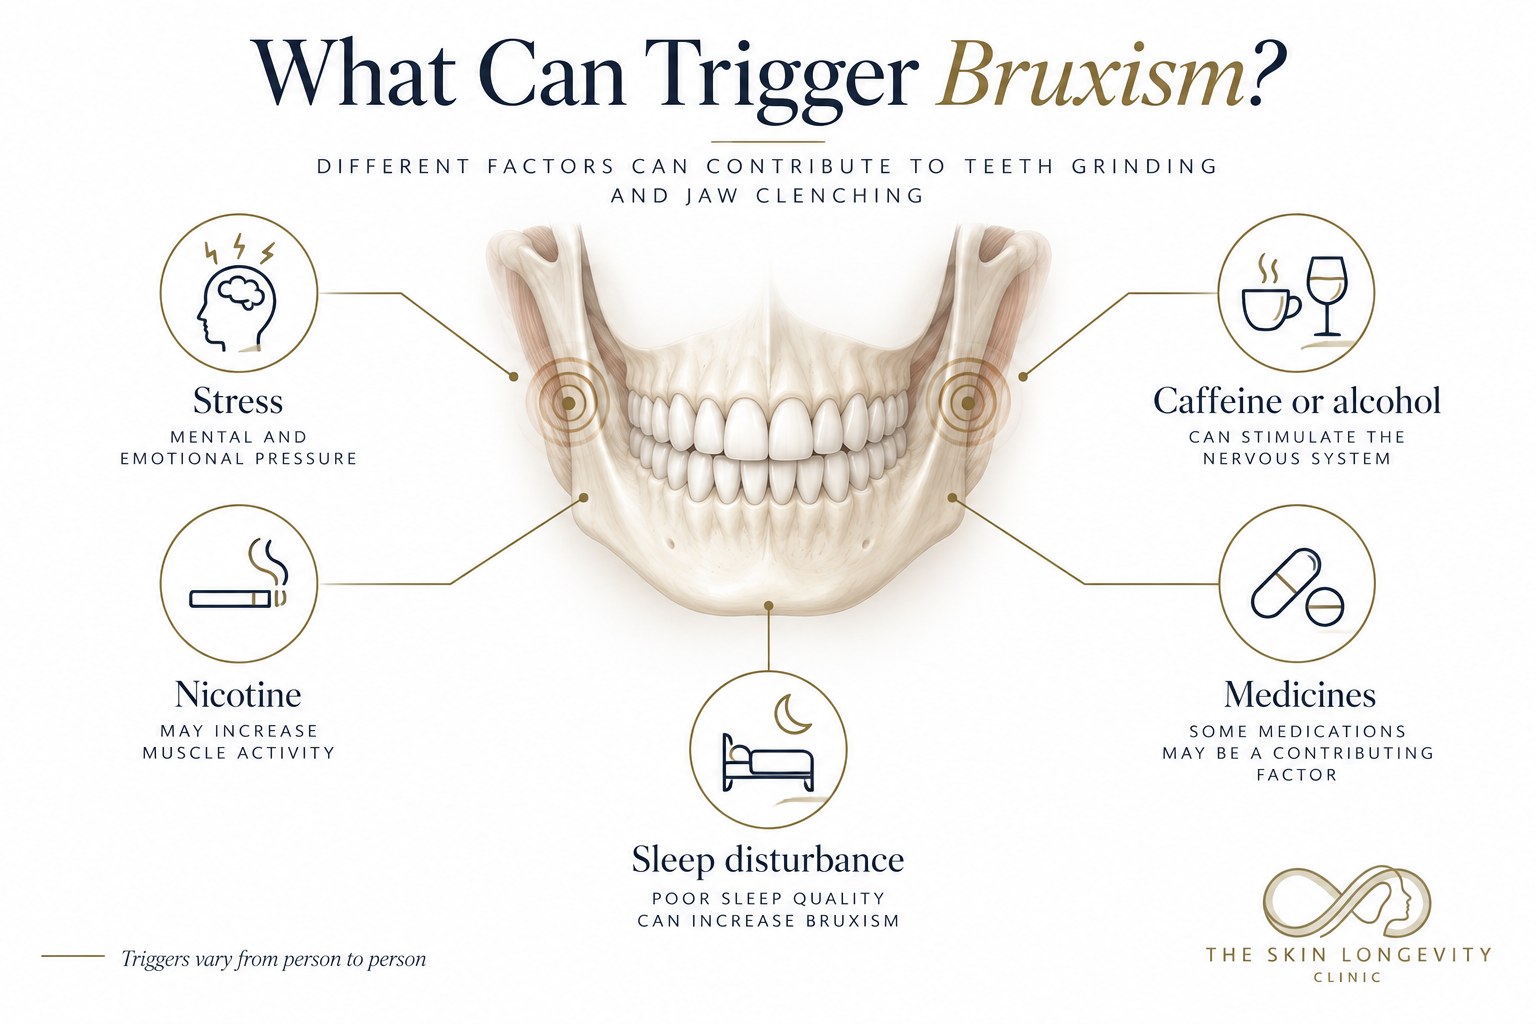
Several factors may contribute, including stress, sleep related arousals, alcohol, caffeine, nicotine and some medicines2,6. These associations vary between people, so a review of your own symptoms and routine is more useful than assuming a single cause3.
Triggers for teeth grinding and jaw clenching vary from person to person.
Sleep bruxism has also been observed in people with obstructive sleep apnoea, although the association does not establish that everyone who grinds their teeth has an airway problem4. Loud snoring, witnessed breathing pauses or daytime sleepiness are reasons to discuss a sleep assessment alongside the jaw concern3,4.
Bring a medication list, particularly when clenching began after a prescription change. Any adjustment should be discussed with the prescribing doctor rather than made independently.
What symptoms should be assessed?
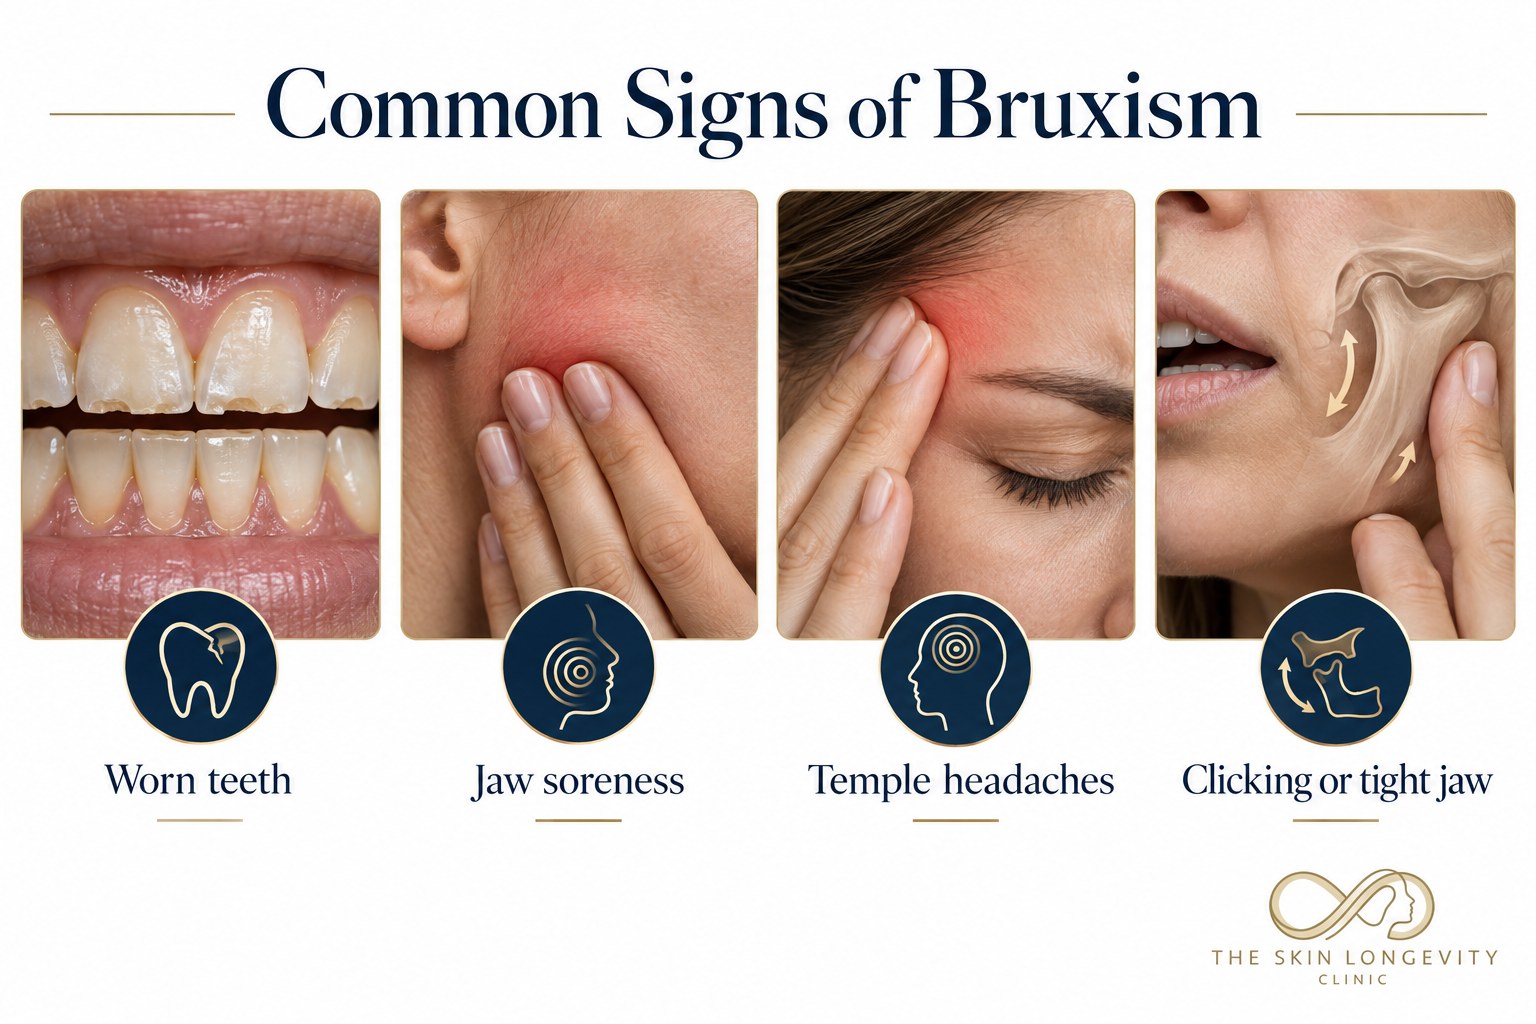
Possible clues include jaw tightness, temple discomfort, tooth sensitivity, chipped or worn teeth and a partner hearing grinding during sleep2. Painful clicking, locking or restricted mouth opening also need assessment because the jaw joint may be involved5.
Common signs that teeth grinding or clenching needs assessment.
A dentist can examine the teeth and restorations, while medical assessment considers muscle symptoms and associated health concerns3,9. Tooth wear should be interpreted alongside the history and examination rather than used alone to describe current bruxism activity1,3.
Is bruxism the same as a TMJ problem?
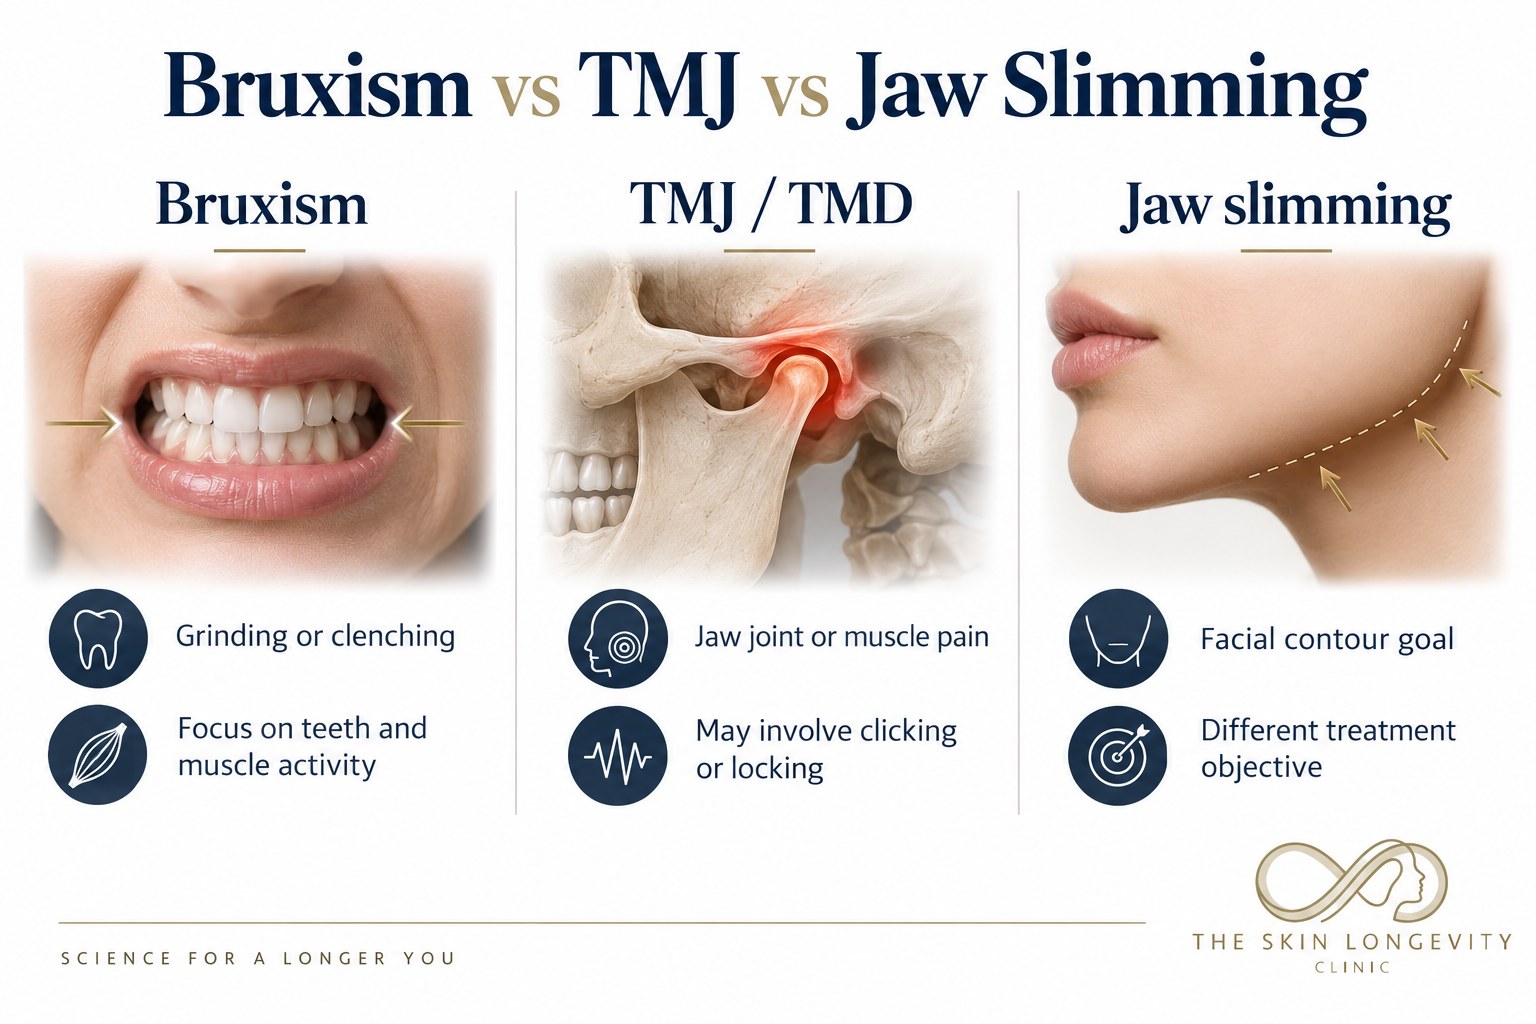
The temporomandibular joint, or TMJ, is the joint in front of each ear; temporomandibular disorders, or TMDs, are conditions affecting the jaw joints or chewing muscles5. Bruxism and TMD can occur together, but their assessment and treatment goals differ1,5.
Painless clicking is common and often needs no treatment5. Pain, locking or a change in movement deserves a closer examination rather than being attributed to clenching without assessment5.
How is bruxism assessed?
Assessment combines your account of the behaviour with examination of its possible consequences3. The discussion should cover when symptoms occur, chewing comfort, previous dental damage, sleep symptoms and treatments already tried3.
A sleep study is considered when it would answer a specific clinical question, rather than being necessary for everyone who clenches1,2. Dental assessment remains important when tooth wear, sensitivity or broken restorations are the main concern2,9.
What helps bruxism?
Protecting teeth, improving comfort and reducing muscle activity are different treatment goals2,6,7. An appropriate plan may combine measures, with progress judged against the problem that prompted the consultation3.
Bruxism care often involves more than one professional.
Mouth guards and dental protection
A dentist may recommend an occlusal splint, commonly called a night guard, to separate and protect the teeth2,9. It can serve that protective role even when some sleep related muscle activity continues6.
The appliance needs an appropriate fit and review5. A guard that causes pain or changes how the teeth meet should be checked rather than worn through the discomfort5.
Awareness and everyday habits
For daytime clenching, brief reminders can help you notice when the teeth are held together and allow the jaw to rest with the teeth apart2. Stress management and reviewing caffeine or alcohol use may also be useful, depending on the factors relevant to you2.
These measures address habits and contributors rather than promising that relaxation will stop all sleep bruxism6. Choose a small number of manageable changes and review whether they improve your comfort.
Physiotherapy and care for jaw pain
When a temporomandibular disorder is present, supervised jaw exercises, selected manual therapies and approaches such as cognitive behavioural therapy have evidence for improving chronic pain or function8. These findings concern TMD symptoms, rather than proving that the same treatments eliminate tooth grinding during sleep6,8.
The exercises should suit the diagnosis and current movement of the jaw5,8. Persistent locking or substantial pain needs assessment before starting a forceful stretching or jaw strengthening routine5.
Reviewing sleep and medical contributors
A sleep physician may be involved when symptoms suggest sleep disordered breathing, while a dentist addresses tooth protection and dental damage4,9. The roles complement one another, and managing an associated condition should not be assumed to remove every component of bruxism4,6.
A shared plan is especially useful when several professionals are involved. It should identify who is reviewing the teeth, the muscle symptoms and any sleep concern.
Where does botulinum toxin fit?
Botulinum toxin has been studied as a way to reduce the intensity of jaw muscle contraction in selected patients7. In a small placebo controlled trial, contraction intensity decreased without a significant reduction in the measured frequency of sleep bruxism episodes7.
This distinction matters: reducing the force of a contraction is different from stopping the activity that produces it7. For TMD pain, study results remain mixed, so an injection should not be presented as the routine answer to every painful jaw5,8.
The potential benefit needs to be weighed against unwanted muscle weakness, effects on chewing and the uncertainties around repeated treatment6,7. Suitability, the exact diagnosis and the locally authorised indication require medical review before any prescription treatment is considered.
Is bruxism treatment the same as jaw slimming?
Bruxism assessment considers muscle activity and its consequences, while masseter hypertrophy describes enlargement of the chewing muscle1,3. Protecting teeth or improving comfort is a different objective from deliberately changing facial contour.
Bruxism, TMD and jaw slimming have different treatment objectives.
Bring details of your symptoms, medicines, previous treatments and any dental reports or appliances. A brief record of when you notice clenching, pain or disturbed sleep can help make the discussion specific.
What to bring to a bruxism consultation.
At The Skin Longevity Clinic, the assessment can help identify which concerns need medical review and when dental or sleep expertise should be involved. Dental appliances and sleep investigations require the relevant provider; the next step should be agreed according to your findings.
Frequently asked questions about bruxism
Can a night guard cure teeth grinding?
A night guard mainly protects the teeth and may influence muscle activity, but it does not reliably eliminate sleep bruxism2,6. Its value should be reviewed through dental protection, fit and symptoms rather than the expectation of a permanent cure5,6.
Should I see a doctor or dentist first?
Tooth sensitivity, fractures or worn restorations are good reasons to begin with a dentist2,9. Jaw pain, medication concerns or symptoms of a sleep disorder may also require medical assessment, with referral based on the findings3,9.
How is improvement measured?
Assessment tools consider symptoms, dental findings, muscle activity and associated factors separately3. We would agree on practical priorities, such as more comfortable chewing or monitoring dental damage, then review whether the plan is meeting them.
Discuss teeth grinding or jaw clenching in Singapore
You can arrange an assessment at The Skin Longevity Clinic to discuss persistent jaw tension or a concern about clenching. Our contact page has appointment information and directions to Scotts Medical Center at Pacific Plaza.
References
Verhoeff MC, Lobbezoo F, Ahlberg J, et al. Updating the Bruxism Definitions: Report of an International Consensus Meeting. Journal of Oral Rehabilitation. 2025;52(9):1335–1342. DOI: 10.1111/joor.13985. Full text.
National Institute of Dental and Craniofacial Research. Bruxism. Reviewed March 2025. Official patient information. NIDCR.
Manfredini D, Ahlberg J, Aarab G, et al. Standardised Tool for the Assessment of Bruxism. Journal of Oral Rehabilitation. 2024;51(1):29–58. DOI: 10.1111/joor.13411. Journal.
Li D, Kuang B, Lobbezoo F, de Vries N, Hilgevoord A, Aarab G. Sleep bruxism is highly prevalent in adults with obstructive sleep apnea: a large scale polysomnographic study. Journal of Clinical Sleep Medicine. 2023;19(3):443–451. DOI: 10.5664/jcsm.10348. PubMed.
National Institute of Dental and Craniofacial Research. TMD (Temporomandibular Disorders). Reviewed September 2026. Official patient information. NIDCR.
Minakuchi H, Fujisawa M, Abe Y, et al. Managements of sleep bruxism in adult: A systematic review. Japanese Dental Science Review. 2022;58:124–136. DOI: 10.1016/j.jdsr.2022.02.004. PubMed.
Shim YJ, Lee HJ, Park KJ, Kim HT, Hong IH, Kim ST. Botulinum Toxin Therapy for Managing Sleep Bruxism: A Randomized and Placebo Controlled Trial. Toxins. 2020;12(3):168. DOI: 10.3390/toxins12030168. PubMed.
Yao L, Sadeghirad B, Li M, et al. Management of chronic pain secondary to temporomandibular disorders: a systematic review and network meta analysis of randomised trials. BMJ. 2023;383:e076226. DOI: 10.1136/bmj-2023-076226. PubMed.
HealthHub Singapore, contributed by NHG Health. Q&A: Teeth Grinding. Official patient information, used for the dental assessment and referral discussion. HealthHub.