


17 Aug Acne Scar Treatment Singapore: Pimple Scar Removal & Treatment Options
By Dr Rachel Ho | Aesthetic Doctor, Founder, The Skin Longevity Clinic, Singapore
Medically reviewed by Dr Rachel Ho, MBBS, MRCS, MMed (ENT), 10 October 2026.
Dr Rachel Ho is an aesthetic doctor and the founder of The Skin Longevity Clinic. She holds an MBBS from the National University of Singapore, the MRCS (Edinburgh) and a Master of Medicine, with more than 16 years of clinical experience spanning facial reconstructive surgery and aesthetic medicine. Her work has been featured in Vogue Singapore, Harper’s Bazaar, CNA Lifestyle and The Straits Times. She also writes about skincare science at drrachelho.com.
Acne may have settled while the texture it left behind still bothers you. A scar consultation begins by identifying those changes and discussing what you would most like to improve.
Acne scar treatment depends on the scar pattern and the concern being addressed8. Rolling scars may need subcision, ice pick scars may respond to TCA CROSS, and boxcar or mixed atrophic scars may be treated with fractional CO2 laser, RF microneedling or a combination8,13. Flat brown or red marks after acne are pigmentation rather than true scars and are treated differently13. This guide covers treatment selection and practical planning, while our scar identification guide explains how the different patterns look.
For readers comparing procedures, the clinic’s fractional RF microneedling guide explains that particular treatment. A consultation should establish its relevance before a course is selected.
Five questions a scar consultation should answer: whether complete removal is realistic, how treatment is chosen, how long a plan may take, what affects cost and how safety is planned for Asian skin.
Acne scar treatment at a glance
| Question | Answer |
|---|---|
| What needs assessment first? | Scar shape, depth, distribution and the distinction between altered texture and colour changes13. |
| How is treatment chosen? | According to the findings, medical suitability and the evidence for the proposed approach8. |
| Can scars be completely removed? | Treatment aims for improvement; the degree of change varies, so complete removal should not be promised13. |
| How many sessions are needed? | Ask for an initial plan and review points rather than treating a published research protocol as a personal guarantee. |
| What affects cost? | The procedures and treatment areas proposed, repeat treatment, and the scope of the quotation. |
What are acne scars, and are yours actually scars?
Acne scars, which many patients in Singapore search for as pimple scars, are permanent structural changes in the dermis left behind after inflamed acne heals. Pimple scars and acne scars mean the same thing, and the advice in this guide applies equally to both. True scars are textural, meaning the skin surface is depressed, tethered or raised. They differ from acne marks, the flat red or brown discolouration that follows a pimple, which usually fades with time and responds to entirely different treatments.
This distinction is the first fork in the road, and getting it wrong wastes both money and downtime. Post-inflammatory erythema (PIE) describes flat red or pink marks caused by dilated capillaries and is more common in fairer skin. Post-inflammatory hyperpigmentation (PIH) describes flat brown marks caused by excess melanin and is very common in Asian skin. Structural scars are actual changes in skin texture, such as depressions, pits, tethering or raised tissue.
A simple check at the mirror can help. Press a clean fingertip or a glass slide over the area. Redness that blanches, meaning it fades with pressure, suggests PIE. Brown staining that persists under pressure suggests PIH. Anything you can see as a shadow under overhead lighting, such as a dent, pit or undulation, is structural. I cover marks in detail in my guide to acne marks vs acne scars. This guide focuses on structural scars.
Scars after surgery or injury, and raised scars that itch or feel tight, may need a different assessment from depressed acne scars. Our scar concern page explains how to prepare for that discussion and find the relevant guide.
One more prerequisite. Active acne must be controlled before scar treatment begins. Resurfacing skin that is still breaking out is like renovating a house while the roof still leaks, because new scars form as fast as old ones are treated. If you are still getting inflamed breakouts, start with our acne assessment and treatment guide.
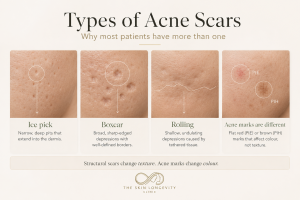
How can you tell acne scars from acne marks? Ice pick, boxcar and rolling scars change the texture and structure of the skin. Red post-inflammatory erythema and brown post-inflammatory hyperpigmentation are flat colour changes and require a different treatment approach.
How scar type guides treatment selection
The three main depressed acne scar patterns are ice pick, boxcar and rolling scars8. Their different shapes help organise the treatment discussion, although an individual assessment still needs to consider the overall skin findings.
Ice pick acne scars
Ice pick scars have a narrow opening and extend more deeply than their small surface size suggests13. Their focal shape is one reason a targeted approach may be discussed rather than relying only on broad resurfacing.
Boxcar acne scars
Boxcar scars have defined edges and a broader base, with variation in depth13. The assessment should distinguish shallower texture changes from deeper individual depressions before discussing treatment.
Rolling acne scars
Rolling scars create broader undulations, with fibrous tethering contributing to their appearance13. Assessment of tethering helps determine whether treatment beneath the depression belongs in the plan.
Raised acne scars
Raised scars need a separate assessment from depressed scars13. Hypertrophic scars stay within the original injury boundary, while keloids extend beyond it13.
Treatment approaches by scar pattern
| Main finding | Approaches that may be discussed | Purpose of the discussion |
|---|---|---|
| Narrow ice pick pits | Focal TCA CROSS or selected punch techniques13. | Address individual deep defects. |
| Shallow boxcar scars and uneven texture | Fractional resurfacing or microneedling approaches8,13. | Discuss changes in edges and surrounding texture. |
| Deeper boxcar scars | Selected focal procedures, sometimes with resurfacing13. | Assess the depth of each defect rather than treating all depressions alike. |
| Tethered rolling scars | Subcision, with other approaches where indicated13. | Address fibrous attachments and reassess residual texture. |
| Raised hypertrophic or keloid scars | A separate raised scar management plan13. | Avoid applying the same plan used for depressed scars. |
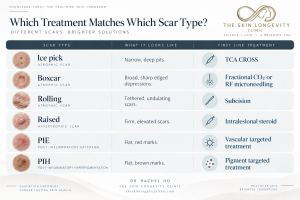
An overview of the approaches commonly discussed for each scar pattern. The plan for any individual follows assessment rather than the label alone.
This table is an overview, rather than a prescription for every scar with the same name. Keep the fuller visual descriptions in the scar identification guide and the treatment discussion on this page.

Why do single acne scar treatments often disappoint? Tethered scars first need release, defined pits and uneven texture need resurfacing, and depleted scar beds can benefit from carefully selected collagen or matrix support. Each step performs a different job.
Why single acne scar treatments disappoint
Almost every disappointed patient who comes to me from elsewhere has the same history. They bought multiple sessions of one treatment, usually a laser, as a package before their scar types were ever mapped. The laser was not the problem. The plan was.
I find it useful to think of comprehensive scar revision as three distinct jobs.
The first job is release. Tethered rolling scars are held down by fibrous bands, and subcision severs these bands so the surface can lift. No energy device does this job well from above.
The second job is resurfacing. Boxcar edges, textural irregularity and shallow pitting respond to controlled dermal injury that triggers collagen remodelling. This is the territory of the fractional CO2 laser and RF microneedling, with TCA CROSS for ice pick pits.
The third job is rebuilding. Atrophic scars sit in a dermis that is thinner and poorer in collagen than it should be. Regenerative injectables, including polynucleotide (PDRN) injections, PDLLA-HA hybrid skinboosters, PLLA collagen biostimulators and ECM skinboosters, supply the biological raw material and stimulus for longer-term dermal repair.
This is not just my preference. A 2026 network meta-analysis of 56 randomised trials covering nearly 1,500 patients found combination treatments generally outperform single treatments for atrophic acne scars, with fractional CO2 laser plus subcision among the most consistently effective pairings2. Not every patient needs all three jobs done. But every patient deserves to know which of the three their scars require before anyone sells them a package.
Which procedures may be considered for acne scars?
Subcision for tethered and rolling scars
Subcision involves releasing fibrous attachments beneath selected depressed scars13. It may form part of a plan when tethering contributes to the contour, with the need for further treatment assessed separately8,13.
Discuss the proposed area, bruising and recovery, and the reason for any additional procedure. A needle or cannula technique should be selected for the individual assessment rather than presented as universally superior.
TCA CROSS for ice pick scars
TCA CROSS uses focal trichloroacetic acid application to create a controlled injury within selected scars13. This is a different procedure from applying a superficial peel across a broader skin area.
The assessment should explain the intended benefit, local healing and the possibility of pigment change13. Ask why this approach is being considered for the particular pits identified, rather than choosing it solely because a scar looks small.
Fractional laser and RF microneedling
Fractional CO2 laser
The fractional CO2 laser is an ablative laser at 10,600nm that creates thousands of microscopic columns of controlled thermal injury, leaving intact skin between them to speed healing. As those columns repair, the dermis remodels. Boxcar edges soften, shallow pits fill and overall texture smooths. Among energy devices it carries the deepest published evidence base for atrophic acne scars.
It suits boxcar scars, shallow atrophic scarring, generalised textural irregularity and enlarged pores. Most programmes involve 3 to 6 sessions, with visible results building over 6 to 12 weeks after each one. Downtime is commonly several days of redness, pinpoint crusting and roughness. Ablative resurfacing carries a real PIH risk in darker skin, so in my practice settings matter more than the machine. I use conservative density and energy, staged treatment and disciplined pigment care before and after each session.
Read more on the clinic’s fractional CO2 laser treatment page. I have also written a broader overview of lasers in aesthetic dermatology on my personal site.
RF microneedling
Radiofrequency (RF) microneedling delivers energy through insulated microneedles directly into the dermis, heating where collagen remodelling is needed while largely sparing the epidermis above, depending on the device and settings. That design is why it has become my preferred resurfacing option for patients at higher PIH risk.
The comparative evidence is worth knowing, and it is unusually consistent. A Cochrane review found that both approaches improved scars by a little over half on average, with no meaningful difference between them, but redness and scaling lasted roughly ten days after the laser versus under a week after radiofrequency, and about one in three patients developed temporary darkening on the laser side while none did on the radiofrequency side1. For darker Asian skin tones that risk profile is often the deciding factor.
It suits rolling and boxcar scars, scarring with skin laxity, PIH-prone skin and patients whose acne is controlled but still flare-prone. Most programmes involve 3 to 5 sessions spaced 4 to 6 weeks apart, with roughly 1 to 3 days of redness and mild swelling. Read more on the clinic’s fractional RF microneedling page.
Selected injectable approaches
The evidence and intended role of an injectable should be considered separately from any release or resurfacing procedure8. Ask what additional concern it is intended to address before adding it to a scar treatment plan.
The clinic’s PDLLA article and ECM evidence article discuss those materials individually. Their inclusion in related reading does not imply that either is needed for every patient. The skin boosters in Singapore page compares the categories side by side.
Polynucleotide (PDRN) injections
Polynucleotides are DNA-fragment biomolecules derived from salmon that act on fibroblasts, support new blood vessel formation and modulate wound repair. They do not add volume. They improve the biological quality of healing tissue. A more viscous polynucleotide formulation is designed specifically for injection beneath depressed scars. Protocols typically involve 3 to 4 sessions spaced 3 to 4 weeks apart, with injection-point bumps visible for 24 to 72 hours. The evidence base is young but genuinely encouraging. A randomised, double-blinded, placebo-controlled study of 20 women with moderate to severe atrophic acne scars found polynucleotide injections meaningfully improved measured dermal quality and patient satisfaction at one and three months, while the saline side did not improve4. It remains a smaller evidence base than lasers command, which is why I position polynucleotides as an adjunct within a combination plan rather than a standalone fix. The clinic’s PDRN skinboosters page covers the treatment itself. I have also compared polynucleotide healers with conventional skinboosters on my personal site.
PDLLA and PLLA collagen biostimulators
Poly-lactic-acid microparticles trigger a controlled foreign-body response that builds new collagen over weeks to months. The family spans three clinically distinct tools. Superficial PDLLA-HA hybrid skinboosters use small, faster-degrading PDLLA particles carried in non-crosslinked hyaluronic acid, delivered as intradermal microdroplets for shallow scars, pores and fine texture, with minimal downtime over 2 to 3 sessions. An open-label prospective trial of intradermal PDLLA delivered over four sessions reported improvement of a little over a third on a validated acne scar scale, with about eight in ten patients satisfied, and biopsies at five months confirmed the particles had biodegraded while collagen and elastic fibres increased6. I wrote an honest guide to PDLLA for acne scars covering this in depth. Volumising PDLLA-HA formulations carry a higher PDLLA ratio with larger particles, placed deeper for atrophic scarring with genuine volume deficit, with results building over 8 to 12 weeks and typically lasting 18 to 24 months. PLLA collagen biostimulators have the longest track record in the family, with FDA approval since 2004 and aesthetic indications added later. Acne scar use is off-label but has been studied since 2007, and a Canadian phase II study of 22 patients reported much-to-excellent improvement in roughly half to two thirds of patients over 3 to 4 sessions, with a single palpable nodule in the whole group5. Placement is deeper, results build over 2 to 3 months, and correction of rolling scars has been reported to last up to four years. A nodule risk exists and is managed with correct dilution, placement and massage.
Choosing within this family is a depth-and-volume decision. The clinic’s collagen biostimulator treatments page covers the category.
ECM (hADM) skinboosters
The most recent arrivals are extracellular matrix (ECM) skinboosters derived from micronised human acellular dermal matrix (hADM), which is decellularised human dermis retaining collagen types I, III, IV and VII along with elastin and matrix proteins. Rather than only signalling repair or stimulating collagen, they deliver matrix components directly while also activating fibroblasts. Typical protocols involve 2 sessions about 4 weeks apart with minimal downtime. The evidence deserves honest framing. A double-blind randomised trial of 202 patients found micronised dermal matrix matched an established collagen filler for facial folds, with biopsies showing collagen deposition and fibroblast activity7, but no dedicated randomised trial has yet tested it against acne scars, and current evidence-based scar guidance does not yet include it. I therefore offer ECM boosters as a promising adjunct for scar-bed quality rather than a proven standalone scar treatment. See our article on ECM skin boosters for acne scars: evidence, suitability and limits.
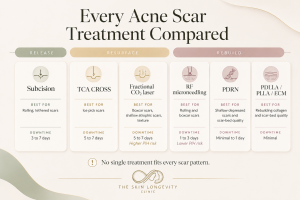
Which treatment suits each acne scar type? Subcision releases rolling scars, TCA CROSS targets narrow ice pick scars, fractional carbon dioxide laser and RF microneedling remodel texture, while PDRN, PDLLA, PLLA and ECM treatments can support selected shallow scars and scar-bed quality.
What is the best laser for acne scars?
No single laser suits every scar. Fractional CO2 laser and RF microneedling both improve atrophic acne scars to a similar degree; in the trials summarised by a Cochrane review, redness lasted longer and temporary darkening was more common after the laser1. For Asian skin at higher risk of post-inflammatory hyperpigmentation, that difference often guides the choice. Combination treatment, such as fractional CO2 laser with subcision, generally outperformed single treatments in a 2026 network meta-analysis2. The fractional CO2 laser and RF microneedling pages explain each treatment.
Every acne scar treatment compared
Every acne scar treatment compared
| Treatment | Job | Best scar types | Typical sessions | Downtime |
|---|---|---|---|---|
| Subcision | Release | Rolling, tethered, distensible | 1 to 5 | 3 to 7 days (bruising) |
| TCA CROSS | Resurface (focal) | Ice pick, small deep boxcar | 2 to 4 | 5 to 7 days (spot scabs) |
| Fractional CO2 laser | Resurface | Boxcar, shallow atrophic, texture, pores | 3 to 6 | 5 to 7 days |
| RF microneedling | Resurface and remodel | Rolling, boxcar, laxity, PIH-prone skin | 3 to 5 | 1 to 3 days |
| Polynucleotides (PDRN) | Rebuild (repair signalling) | Shallow depressed scars, scar-bed quality | 3 to 4 | Bumps 24 to 72 hours |
| PDLLA-HA skinbooster (superficial) | Rebuild (collagen) | Shallow scars, pores, fine texture | 2 to 3 | Minimal |
| PDLLA-HA (volumising) | Rebuild (collagen and volume) | Atrophic scars with volume loss | 2 to 3 | Minimal to mild |
| PLLA biostimulator | Rebuild (collagen and volume) | Rolling or atrophic with broader deficit | 2 to 3 | Minimal to mild |
| ECM (hADM) skinbooster | Rebuild (matrix) | Scar-bed quality, early evidence | 2 | Bumps 24 to 48 hours |
Planning treatment and recovery
Ask which scars are the first priority, what the initial treatment is intended to change and when that response will be reviewed. The number and order of procedures should follow the findings rather than a standard sequence assumed to suit everyone. Active acne is controlled before scar work begins; selective sebaceous gland ablation for acne is one of the options assessed at that stage.
Bring details of previous procedures, medicines and reactions, and explain any constraints involving work, photographs or travel. The consultation can then address recovery and scheduling alongside the intended result.
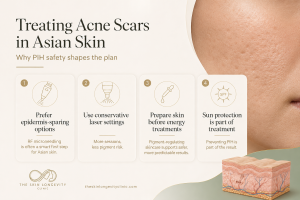
Is acne scar treatment safe for Asian skin? Treatment can be performed safely when post-inflammatory hyperpigmentation risk is planned for. Epidermis-sparing options, conservative energy settings, pigment preparation, suitable treatment intervals and sun protection all influence recovery.
Treating acne scars in Asian skin
Most of my patients are Fitzpatrick type III to V, and pigmentary safety shapes every plan I write. Melanin-rich skin responds to aggressive thermal injury with post-inflammatory hyperpigmentation, and trading dents for dark patches is not a good bargain.
In practice that means preferring epidermis-sparing technology such as RF microneedling where PIH risk is high, running ablative lasers at conservative density and energy over more sessions rather than maximal settings over few, preparing skin with pigment-regulating care before energy treatments where indicated, and treating sun protection as part of the prescription rather than an afterthought. Slower, in Asian skin, is very often faster.
What affects the cost of acne scar treatment in Singapore?
A useful acne scar quotation should identify the areas being treated and the purpose of each proposed procedure. Treatment of a few individual pits and a plan addressing several areas can involve different components, so the session price alone may be an incomplete comparison.
Ask how the initial plan will be reviewed before further treatment is recommended. Any subcision, TCA CROSS, resurfacing or injectable component should have a clear role and an understandable cost.
| Quotation detail | What to ask |
|---|---|
| Treatment area | Which scars and facial areas are included? |
| Proposed techniques | What is each procedure intended to address, and is it optional or part of the initial recommendation? |
| Preparation and comfort measures | Which items are included and which are charged separately? |
| Staged or combined treatment | Are procedures proposed together or at separate appointments? |
| Aftercare and review | Are aftercare products and review appointments included? |
| Further sessions | What would another session cost, and what finding would justify it? |
| Quoted total | Does the estimate include any applicable taxes and additional charges? |
Bring the names of previous scar treatments and describe both the response and the recovery. This information can make the quotation discussion more specific than comparing packages that may treat different concerns.
Arrange a scar assessment enquiry to discuss suitability and the information needed for a personalised estimate. Ask for the proposed stages and their costs to be explained before committing to a course.

Improvement varies with the scars and the treatment used. Results are reviewed once healing and remodelling have had time to occur, rather than judged in the first weeks.
Can you get rid of acne scars completely?
Acne scar procedures aim to improve appearance, with the response varying by the scars and treatment used8,13. A useful consultation should explain what change is being sought and how the response will be assessed.
Discuss the difference between early healing and the point at which the treatment result can be reviewed. A percentage reported in a particular study should be interpreted alongside that study’s patients, scoring method and follow up, rather than converted into a promise for your skin.
Common questions about pimple scar treatment
What is the best acne scar treatment for my skin?
The choice begins with the scar assessment, because the available procedures address different findings8. Ask why the proposed treatment matches your scars and what alternatives deserve consideration.
Can old acne scars still be assessed for treatment?
Older scars can still be assessed alongside their current depth, texture and the surrounding skin13. Bring details of previous procedures so the next discussion can consider what has already been tried and what remains.
How many treatment sessions will I need?
An initial estimate should explain the proposed procedures and when the response will be reviewed. Further treatment should be discussed against that response rather than assumed from a fixed package.
How can acne scars be removed from the face?
In practice, pimple scar removal means improvement rather than erasing every scar. Treatment is matched to the pattern: subcision releases tethered rolling scars, TCA CROSS treats narrow ice pick scars, and fractional resurfacing improves boxcar scars and texture8,13. Creams and peels sold for acne scars mainly help flat marks, not depressions13. Our guide to types of acne scars explains each pattern.
Can acne scars be treated while acne is still active?
Active acne is controlled first, because new scars can form while older ones are being treated8. Isotretinoin does not automatically rule out every procedure: a 2017 consensus found insufficient evidence to justify routinely delaying some procedures, including fractional ablative laser9. Timing is decided individually.
Selected References
- Abdel Hay R, et al. Interventions for acne scars. Cochrane Database of Systematic Reviews. 2016;4:CD011946. doi:10.1002/14651858.CD011946.pub2
- Ou Y, et al. Laser, microneedling, and combination therapies for moderate to severe acne atrophic scars: a systematic review and network meta-analysis. Aesthetic Plastic Surgery. 2026. doi:10.1007/s00266-026-06165-8
- Nilforoushzadeh MA, et al. Comparing cannula-based subcision with the common needle method: a clinical trial. Skin Research and Technology. 2020;26(1):39-44. doi:10.1111/srt.12761
- Araco A, Araco F. Preliminary prospective and randomized study of highly purified polynucleotide vs placebo in treatment of moderate to severe acne scars. Aesthetic Surgery Journal. 2021;41(7):NP866-NP874. doi:10.1093/asj/sjab125
- Sapra S, et al. A Canadian study of the use of poly-L-lactic acid dermal implant for the treatment of hill and valley acne scarring. Dermatologic Surgery. 2015;41(5):587-594. doi:10.1097/DSS.0000000000000366
- Hyeong JH, et al. Intradermal injection of poly-D,L-lactic acid using microneedle fractional radiofrequency for acne scars: an open-label prospective trial. Dermatologic Surgery. 2022;48(12):1306-1311. doi:10.1097/DSS.0000000000003627
- Zhang C, et al. Safety and efficacy of micronized acellular dermal matrix injection for correction of moderate to severe nasolabial folds: a double-blind, multicenter, randomized controlled, non-inferior clinical trial. Aesthetic Plastic Surgery. 2026;50(10):3710-3719. doi:10.1007/s00266-025-05494-4
- Kim EY, Wong JH, Hussain A, Khachemoune A. Evidence based management of cutaneous scarring in dermatology part 2: atrophic acne scarring. Archives of Dermatological Research. 2024;316:19. Published online 7 December 2023. doi:10.1007/s00403-023-02737-9
- Spring LK, et al. Isotretinoin and timing of procedural interventions. JAMA Dermatology. 2017;153(8):802-809. doi:10.1001/jamadermatol.2017.2077
- Leheta T, et al. Percutaneous collagen induction versus full-concentration trichloroacetic acid in the treatment of atrophic acne scars. Dermatologic Surgery. 2011;37(2):207-16. doi:10.1111/j.1524-4725.2010.01854.x
- Yi K-H, Rosellini I, Lee S, Lee HE. Gas subcision with PDLLA (Juvelook): Evaluating a hybrid mechanical-biologic approach for atrophic acne scars. JPRAS Open. 2026;51:129–133. PMID 42389218.
- Dastgheib M, Heidari S, Azizipour A, et al. Investigating the impact of added Profhilo mesogel to subcision versus subcision monotherapy in treating acne scars: a single-blinded, split-face randomized trial. Journal of Cosmetic Dermatology. 2024;23(6):1992–2000. doi:10.1111/jocd.16258.
- Fabbrocini G, Annunziata MC, D’Arco V, et al. Acne Scars: Pathogenesis, Classification and Treatment. Dermatology Research and Practice. 2010;2010:893080. doi:10.1155/2010/893080.
This article is for general information and does not replace a medical consultation. To discuss your own scar pattern, book a consultation at The Skin Longevity Clinic, 9 Scotts Road, #06-05 Scotts Medical Center, Pacific Plaza, Singapore 228210, tel +65 6514 2688, or via the contact page.